

The American Medical Association asked nearly 1,700 physicians about AI this spring. 81% now use it in practice, more than double the rate in 2023. Most think it makes them better doctors. And 88% are worried it's costing them their skills.
Here’s the part that should stop you. That worry is highest among physicians with ten years or less in practice. The people you assumed would adopt fastest, the ones who trained alongside these tools, are the most afraid of what the tools are doing to them.
That’s not a technology problem. You can’t patch it with a better model or a smoother integration. It’s a transition problem, and most health systems have no line item for it.
Change and transition are not the same thing
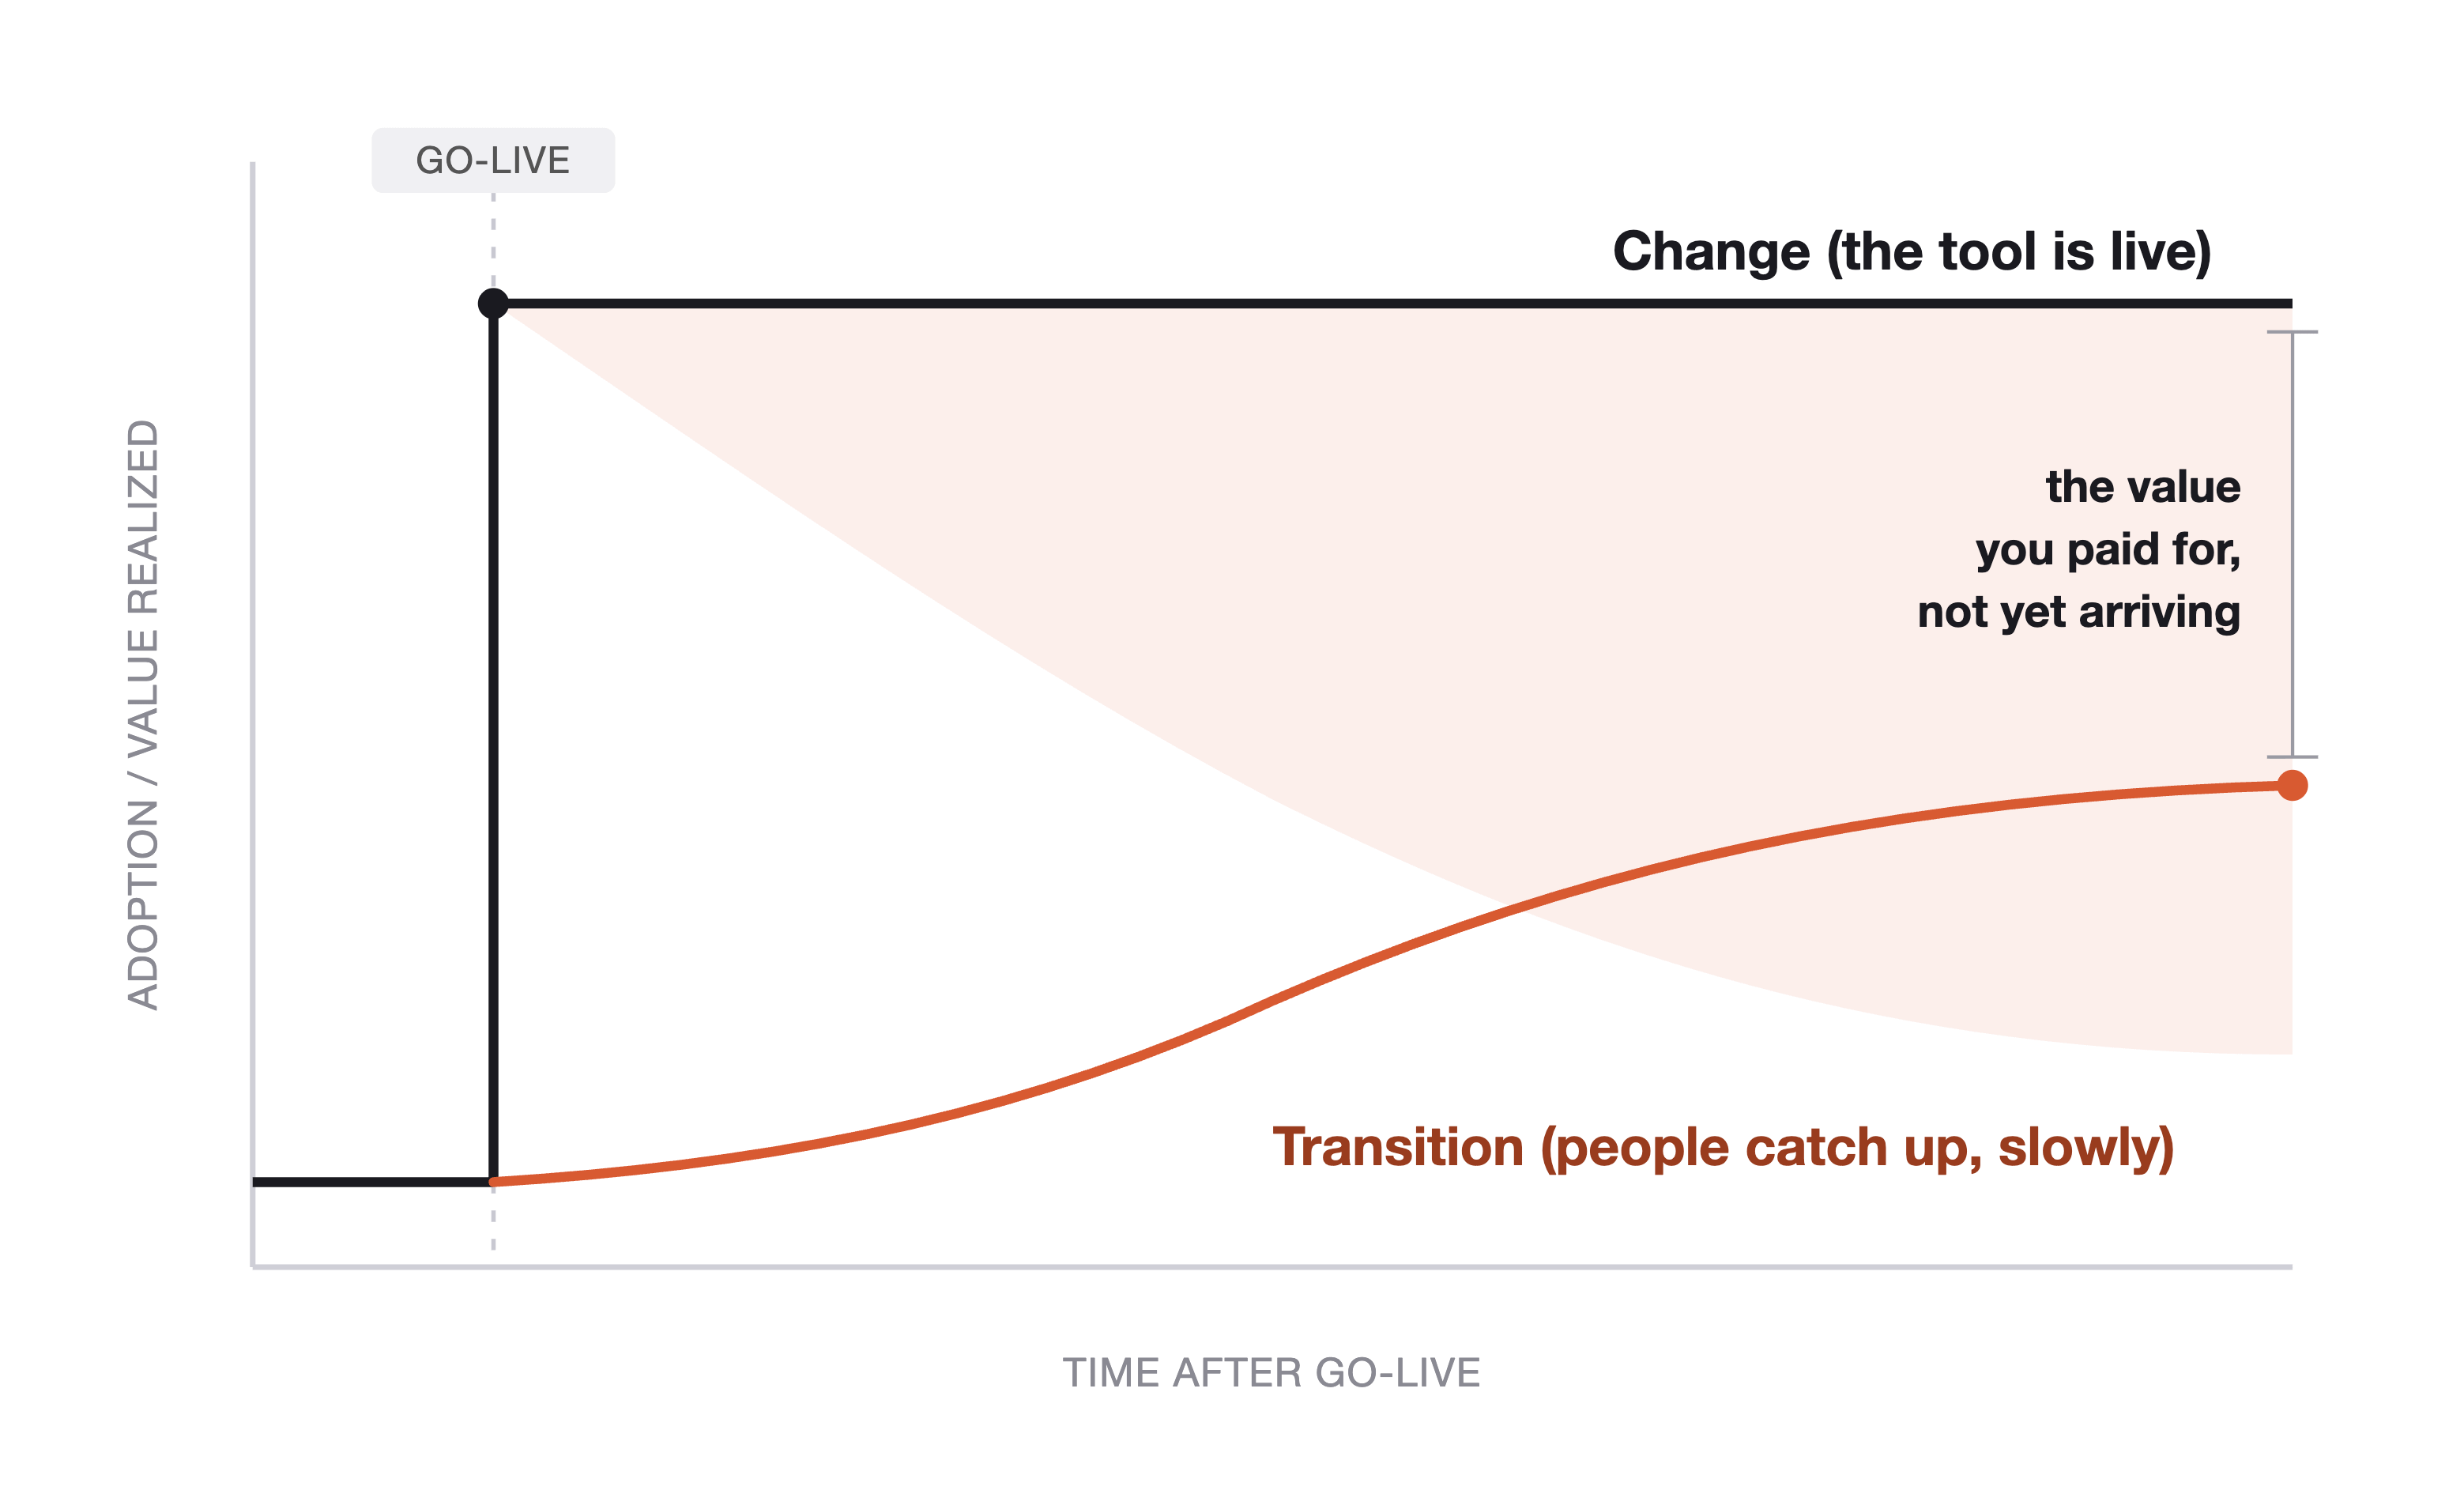
I keep coming back to a distinction from William Bridges, the change consultant who spent forty years on this. Change is external. It’s the new tool, the go-live date, the workflow diagram. Transition is internal. It’s the psychological process a person goes through to come to terms with the change. Change can happen in an afternoon. Transition takes months, and it starts with letting go of the old way of working.
Bridges’ core point: change fails when you manage the change and ignore the transition. You install the new thing, you announce it’s live, and you act surprised when people don’t move with it. They’re still in the gap between the old role and the new one. Nobody helped them across.
This is the gap healthcare keeps falling into with AI. We fund the change. We schedule the go-live, we run the training session, we count the licenses. The transition, the part where a radiologist or an intensivist actually renegotiates what their judgment is worth now that a machine offers an opinion first, gets nothing. No budget, no owner, no plan.
The threat is to identity, not accuracy
The evidence that this is real, and not just soft talk, is better than most leaders think.
Nora Arvai and colleagues at the Medical Futurist Institute reviewed the literature on why clinicians resist medical AI. They pulled 32 studies and mapped the negative attitudes on a scale: skepticism, reluctance, anxiety, resistance, fear. Then they traced where those attitudes come from. The sources split into two groups. The extrinsic ones are about patients and the effect of AI on care. The intrinsic ones are about the clinician’s own identity, their tasks, their sense of competence. That intrinsic group is professional identity threat, and it’s the one most adoption plans never touch.
Read that against the AMA number and the picture sharpens. The youngest clinicians aren’t resisting AI because they don’t understand it. They’re resisting because they understand exactly what it does to a professional identity that isn’t fully built yet. Carl Preiksaitis, an emergency physician at Stanford, gave it a name this year: never-skilling. Deskilling is losing a skill you had. Never-skilling is never building it, because the AI did the reasoning before you got the reps. His example is an ambient scribe that writes a flawless note while the resident, standing there, still can’t say what’s wrong with the patient. The note is perfect. The learning didn’t happen.
The threat is also partly something you design. Sophia Ackerhans and colleagues ran a controlled experiment with 292 medical students and physicians on a sepsis decision-support tool, varying how it was built. Deep integration into the workflow raised trust and lowered the identity threat. But making the physician personally sign off on each AI-influenced decision raised the threat sharply. Even explainability, the feature everyone treats as a pure good, cut both ways: it built trust and raised threat at the same time. How you roll the tool out changes whether clinicians feel supported or cornered, independent of how accurate it is.
None of this is new. Ekaterina Jussupow and colleagues documented the same identity-threat mechanism back in 2022, before any of these tools were in real clinical use. What's changed is that the tools are now live, and the threat stopped being theoretical. It's measurable, it splits into known components, and some of it is under your control at deployment time. Which makes ignoring it a choice, not an oversight.
Why this stays invisible
I wrote earlier this year that we talk constantly about AI safety and almost never about AI status loss. One is technical. The other is political. Safety has frameworks, committees, and a budget. Status loss has none of that, because admitting it exists means admitting that a deployment can be technically perfect and still fail because of how it made people feel about their own worth.
That admission is uncomfortable for a procurement process built to evaluate performance. A benchmark can’t see a radiologist quietly deciding that the AI has made their read a formality. A go-live checklist can’t measure an intensivist who signs off on the algorithm’s call without engaging because the system told them they’re now accountable for a decision they didn’t make. The tool works. The transition didn’t happen. The value never arrives.
This is the same failure I described in The Installation Trap, but one layer deeper. There the missing piece was workflow redesign. Here it's the human one underneath it. You can redesign the workflow perfectly and still lose, because the person inside the new workflow never crossed from their old identity to the new one.
A diagnostic you can run this week
Pull your last AI deployment. Find the person whose job was the clinical transition, not the technical go-live. Not the IT lead who integrated it, not the champion who demoed it. The person responsible for helping clinicians let go of the old way and rebuild their sense of what they’re for. If you can’t name that person, you funded the change and skipped the transition, and the gap between what you bought and what you’re getting is sitting in that hole.
A bigger training budget won't close this. Training is just more change, it teaches people the new tool. Transition is the slower work of helping a profession renegotiate its own value, and it needs an owner, a timeline, and the same seriousness you give the technical rollout.
Bridges had one line that healthcare leaders should sit with. Change is situational. Transition is psychological. You’ve been buying the first and assuming the second comes free.
It doesn’t. And the cost of skipping it isn’t just a stalled deployment. Think about what never-skilling means at scale. A generation of clinicians who trained with the AI doing the reasoning, who never built the judgment to catch it when it’s wrong. You’re not just failing to realize value. You’re deploying tools that quietly hollow out the one safeguard that makes them safe to use: a human who can still tell when the machine is wrong.
That’s the transition nobody budgeted for. Not the soft work of helping people feel better about change. The hard work of making sure the next generation of doctors can still practice medicine without the AI, so they can practice it well with it.
What did the transition cost on your last deployment, and who paid it? Hit reply. I read every response.
Second Opinion is a weekly newsletter for healthcare leaders making AI decisions. Written by Jan Beger, Global Head of AI Advocacy at GE HealthCare and Executive Director of HelloAI. Views are my own and don’t represent the position of GE HealthCare or any other organization I’m affiliated with.
Competence does not form by receiving better answers. It forms in the uncomfortable interval where an answer has to be attempted, held, and corrected before it is confirmed. From outside, that interval looks like inefficiency. From inside, it is where judgment is built. Never-skilling is what happens when assistance arrives early enough to remove it.
The resident sees the finished note and the plausible next step, but skips the part where you have to hold uncertainty long enough to commit to a judgment before help appears. The note is perfect. The rep never happened.
That is why your change-and-transition distinction matters. The real question is not whether clinicians accept AI. It is whether the profession protects a zone where judgment can still form before it is assisted. The missing budget line is apprenticeship: someone has to decide which parts of the work can safely get easier, and which have to stay hard long enough to teach, so a younger doctor can question the tool from a judgment that is actually their own.